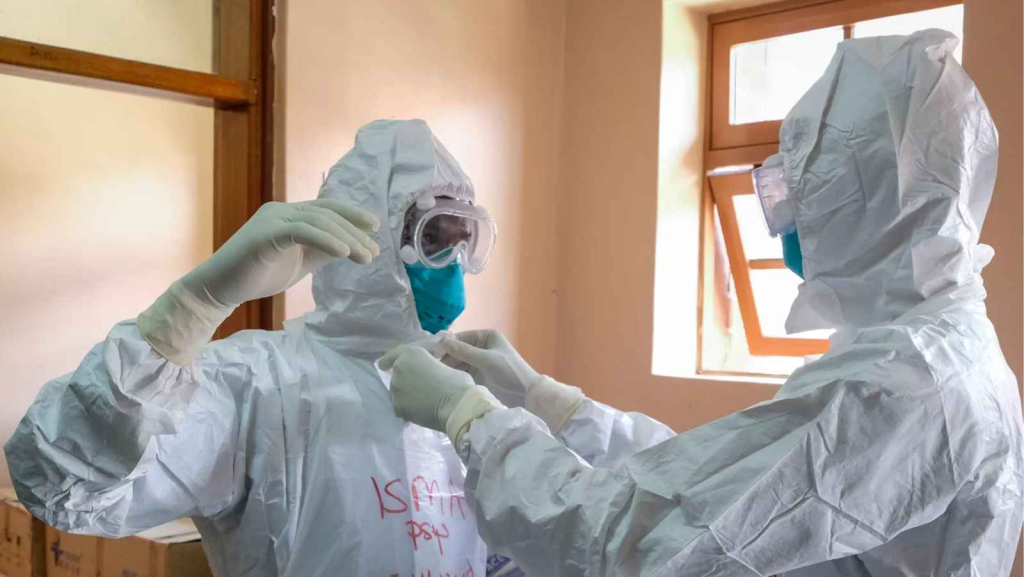
Ebola: A virus that refuses to disappear

By Chioma Obinna WHEN late Dr Ameyo Stella Adadevoh insisted that Patrick Sawyer be isolated at a Lagos hospital in July 2014, she was confronting a disease Nigeria had never experienced on that scale. The reported confirmation on October 20, 2026, of an imported case of Bundibugyo virus disease in a woman who travelled from Uganda and was admitted to a private hospital in Abuja has brought the disease back into focus.
By Chioma Obinna WHEN late Dr Ameyo Stella Adadevoh insisted that Patrick Sawyer be isolated at a Lagos hospital in July 2014, she was confronting a disease Nigeria had never experienced on that scale. Her decision to trust her clinical judgement, despite the pressure surrounding the patient, became a defining moment in the country’s fight against Ebola.
Adadevoh recognised the danger, alerted the authorities and helped trigger the response that eventually contained the outbreak. She contracted the virus and died on August 19, 2014. Nigeria recorded 20 Ebola cases and eight deaths during the outbreak. The country was declared free of Ebola transmission by the World Health Organisation on October 20, 2014.
More than a decade later, Ebola continues to challenge public health systems. The reported confirmation on October 20, 2026, of an imported case of Bundibugyo virus disease in a woman who travelled from Uganda and was admitted to a private hospital in Abuja has brought the disease back into focus. A threat that remains Why does Ebola remain such a formidable threat despite advances in medicine, surveillance and outbreak response?
The answer lies in the virus’s biology, limited treatment options for some species, exposure to infected wildlife, international travel and weaknesses in health systems. Fear, misinformation and distrust can further undermine efforts to control outbreaks. Adadevoh’s story remains relevant because Ebola’s first encounter with a health system may not appear extraordinary.
It may begin with a patient whose symptoms resemble those of a familiar illness and a doctor who must decide whether to look beyond the obvious. The danger behind familiar symptoms For Dr Rotimi Adesanya, a family physician and public health expert, Ebola is dangerous because it can rapidly overwhelm the body. “Ebola Virus Disease is one of the most dangerous infectious diseases known to mankind because of its ability to overwhelm the body’s immune system and cause severe damage to multiple vital organs within a relatively short period,” he said.
Early symptoms include fever, headache, weakness, muscle and joint pain, sore throat and fatigue. More severe symptoms, including vomiting, diarrhoea and abdominal pain, may follow. These symptoms can resemble malaria, typhoid and other common infections, making a patient’s travel history and possible exposure important parts of clinical assessment.
Symptoms generally appear between two and 21 days after exposure. According to the Nigeria Centre for Disease Control and Prevention (NCDC), Ebola spreads through direct contact with the blood or other bodily fluids of infected people or deceased patients, infected animals, or contaminated materials. Early identification, laboratory confirmation, isolation, contact tracing and strict infection prevention and control measures are essential to containing outbreaks.
Adesanya cautioned against the belief that every infected person must bleed visibly. “Contrary to popular belief, not every Ebola patient experiences bleeding. In fact, severe dehydration, shock and multiple organ failure are among the major causes of death.” “Vomiting and diarrhoea can cause substantial fluid and electrolyte loss, resulting in dehydration, falling blood pressure and shock.
The disease can also damage the liver, kidneys and other organs.” Waiting for bleeding before suspecting “Ebola can therefore be dangerous. Patients may need urgent medical intervention before advanced symptoms appear, while exposed individuals may need to be identified and monitored. “Early diagnosis saves two lives. The life of the infected patient and potentially the lives of others who might otherwise become infected,” Adesanya said.
The lesson from Adadevoh’s experience is not that every fever should be treated as Ebola, but that clinicians must consider relevant exposure risks and promptly assess suspected cases through appropriate medical and public health channels. Why Ebola outbreaks keep returning Containing an outbreak does not mean the virus has been eradicated. Ebola is a zoonotic disease, meaning it can pass from animals to humans.
As long as Ebola viruses continue circulating in their natural environment, further spillover into human populations remains possible. According to Adesanya, certain fruit bats are considered likely natural reservoirs for some Ebola viruses, although their ecology and the precise pathways of transmission are not fully understood. Human infection may occur through contact with infected wildlife or their bodily fluids.
Once the virus enters the human population, it can spread through direct contact with the blood or other bodily fluids of infected people, including deceased patients, or through contaminated materials. In an interview with Vanguard, Adesanya identified several factors that make outbreaks difficult to prevent. Surveillance systems may be weak in remote communities where healthcare and laboratory services are limited.
Conflict an
- ebola
- virus
- disease
- patient
- symptom
- health
- adadevoh
- outbreak